

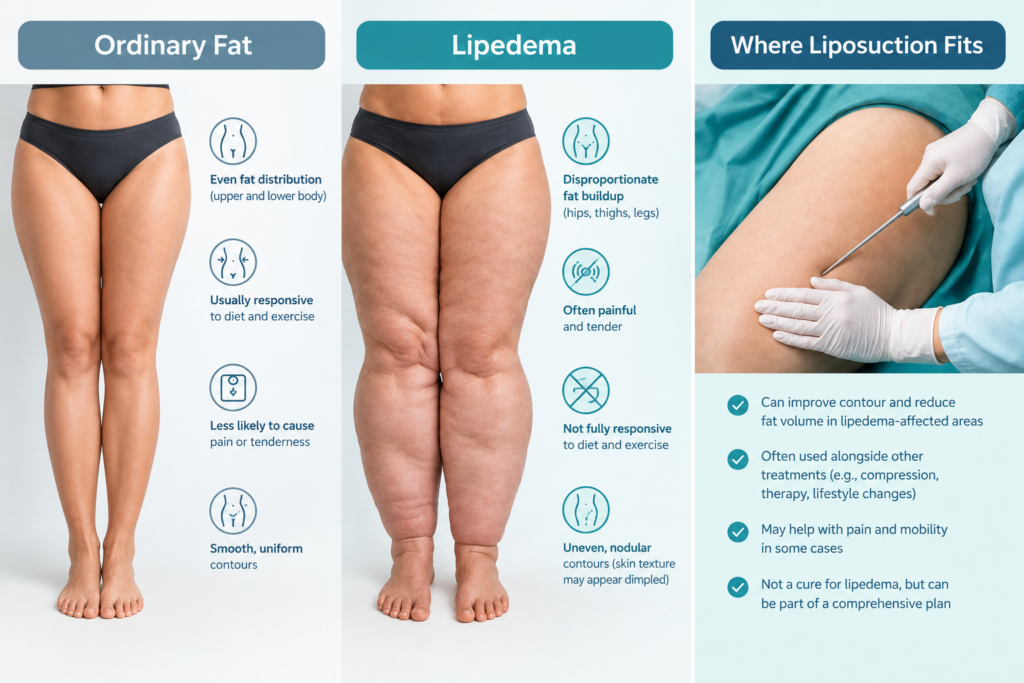
Lipedema is a chronic condition in which fat accumulates abnormally and symmetrically, usually in the legs and often the arms, and characteristically spares the hands and feet. It is painful or tender to touch, bruises easily, and does not respond to dieting the way ordinary fat does.
Ordinary fat is distributed according to your genetics and energy balance, is not painful, and reduces when you lose weight even if it reduces unevenly and slowly.
The most useful distinguishing sign is the cut-off. In lipedema, enlarged tissue stops abruptly at the ankle or wrist, leaving a normal foot or hand below it. That pattern is unusual in ordinary weight gain.
Why this distinction matters
Many people spend years being told to try harder. They diet, they train, the upper body responds, and the legs stay the same or get worse. That experience is common enough among people eventually diagnosed with lipedema that it is worth taking seriously rather than treating as a motivation problem.
Getting the label right changes what you do next. Ordinary diet-resistant fat deposits may be reasonable candidates for contouring. Lipedema needs a different conversation, including conservative management, symptom control, and a specific surgical technique if surgery is considered at all.
It also matters because lipedema is frequently mistaken for two other things: simple obesity and lymphoedema. The management of all three differs.
What lipedema actually is
Lipedema is a disorder of adipose tissue. It affects women overwhelmingly, and onset is commonly described around hormonal transitions such as puberty, pregnancy or menopause, which is one reason a hormonal contribution is suspected. It frequently runs in families.
The fat itself behaves differently. It is described in the literature as nodular and fibrotic, which is why the tissue can feel lumpy or granular under the skin rather than soft. There is also a fluid component, which is part of why the condition is sometimes described as painful swelling rather than simply extra fat.
The most consistently cited diagnostic features are a bilateral and symmetrical build-up of fat in the limbs or lower trunk that resists diet, exercise and even bariatric surgery, with the hands and feet typically spared — sometimes producing a visible cuff at the ankle or wrist.
Signs that point towards lipedema
No single sign confirms it. Clinicians look at the pattern as a whole.
- Symmetry. Both legs, or both arms, affected to a similar degree. Lipedema is not usually one-sided.
- Sparing of hands and feet. The enlargement stops at the ankle or wrist. A normal-looking foot below a heavy calf is one of the more recognisable presentations.
- Disproportion. The lower body appears considerably larger than the upper body, and this proportion persists regardless of weight change.
- Pain and tenderness. Aching, heaviness, or discomfort on pressure. Ordinary fat does not hurt.
- Easy bruising. Bruises appearing with minimal or no remembered injury.
- Texture. A nodular or pebbled feel within the tissue, sometimes described as small beads under the skin.
- Resistance to weight loss. Weight loss reduces the upper body while the affected areas change comparatively little.
- Family history. Other female relatives with a similar body pattern.
Lipedema, ordinary fat and lymphoedema compared
| Feature | Ordinary fat | Lipedema | Lymphoedema |
|---|---|---|---|
| Symmetry | Follows individual distribution | Bilateral and symmetrical | Often one-sided |
| Feet and hands | Involved in proportion | Typically spared | Commonly involved |
| Pain | Not painful | Tender or painful | Usually not painful early |
| Bruising | Normal | Bruises easily | Normal |
| Response to weight loss | Reduces | Comparatively resistant | Not primarily fat |
| Stemmer sign | Negative | Negative | Often positive |
| Texture | Soft | Nodular or fibrotic | Firm, may pit |
The Stemmer sign is a simple clinical check in which the examiner attempts to pinch and lift a fold of skin at the base of the second toe or finger. Difficulty lifting that fold is described as a positive sign and points towards lymphoedema. It is one of several findings used to distinguish the two conditions, not a standalone test, and it should be interpreted by a clinician.
It is also worth knowing that these conditions can coexist. Long-standing lipedema can be accompanied by a lymphatic component, sometimes described as lipo-lymphoedema, which changes the management approach again.
Stages, and why they are useful rather than absolute
Lipedema is commonly described in stages based on skin surface and tissue changes. In broad terms, early stage involves smooth skin over enlarged subcutaneous fat, while later stages involve an increasingly uneven skin surface with nodules and larger deformity.
Staging is clinically useful for describing severity and tracking change, but it is a description rather than a precise measurement, and it does not map neatly onto how much discomfort a person experiences. A 2025 paper proposed adding intermediate stages to allow more precise classification, which reflects that the existing system is a working framework rather than a settled one.
Someone at an early stage may have significant pain. Someone at a later stage may have adapted. Stage alone does not determine what treatment is appropriate.
Why diet and exercise do not resolve it
This is the point that causes the most distress, and it deserves a direct answer.
Diet and exercise reduce fat stores across the body, but the affected lipedema tissue does not respond proportionately. People frequently describe losing weight from the face, chest and abdomen while the legs remain largely unchanged, which can make the disproportion look worse rather than better.
That does not make diet and exercise pointless. Maintaining a stable healthy weight, staying active, and managing any co-existing obesity all remain worthwhile — both for general health and because additional ordinary fat sits on top of the lipedema tissue and does respond.
The realistic framing is that lifestyle measures manage the modifiable part and support overall health. They do not remove the lipedema tissue itself.
Conservative management comes first
Non-surgical management is the foundation, and it is not simply a waiting room before surgery.
- Compression garments to manage swelling, heaviness and discomfort.
- Movement, with low-impact activity such as walking, swimming or cycling often tolerated well.
- Manual lymphatic drainage and complex decongestive therapy, particularly where there is a fluid or lymphatic component.
- Skin care, since tissue changes can affect skin integrity.
- Weight stability, to avoid additional ordinary fat compounding the picture.
- Psychological support, which is frequently overlooked. Years of being told the problem is willpower takes a toll.
These measures address symptoms and can slow deterioration. They do not remove the abnormal fat, which is where surgery enters the discussion.
Where liposuction fits
Liposuction is currently the main surgical option discussed for lipedema, and the technique matters more here than in cosmetic contouring.
The approach described in the literature is lymph-sparing liposuction, generally performed with the tumescent technique. The reasoning is anatomical: the lymphatic vessels in the affected tissue must be preserved, because damaging them risks worsening the fluid component of the condition. Comparative work has indicated that tumescent and water-assisted approaches disturb lymphatic tissue less than dry liposuction, which is why the fluid-based techniques are preferred.
An international consensus conference has addressed the use of liposuction with tumescent local anaesthesia specifically in the context of preventing progression of lipedema, and reported long-term benefit in symptom relief. Reported follow-up in several German series extends to around eight years.
The honest caveat, stated in the literature itself, is that the evidence base remains limited. Reviews note that larger prospective controlled studies are needed before the strength of these findings can be described as robust. Anyone presenting liposuction for lipedema as a settled, proven cure is overstating what is currently known.
Practically, this also tends to be staged surgery rather than a single procedure, because the volumes involved and the areas affected are often extensive. Our guide to the different liposuction techniques and how they differ explains the technique distinctions in general terms, and our overview of liposuction safety and how risk is managed covers why volume and staging decisions matter.
What liposuction for lipedema does not do
Setting this out plainly prevents disappointment.
- It is not a cure. Lipedema is chronic. Surgery addresses the accumulated tissue, not the underlying tendency.
- It does not replace conservative management. Compression and other measures generally continue afterwards.
- It is not weight-loss surgery. As our article on how much weight liposuction actually removes explains, the change in scale weight is modest even when volume removed is substantial.
- It does not guarantee that further tissue will not accumulate over time.
- It does not address a co-existing lymphoedema component, which needs its own management.
Getting properly assessed
Lipedema is diagnosed clinically, through history and examination rather than a single definitive test. That makes the quality of the assessment important.
Useful preparation includes photographs over time if you have them, a record of your weight history and how your body responded to weight change, a note of when the disproportion began and whether it coincided with a hormonal transition, family history, and a clear description of pain, heaviness and bruising.
If your primary concern is a localised, non-painful fat deposit that has resisted diet and exercise, that is a different conversation, and our guide to what makes someone a suitable liposuction candidate covers it. If the pattern described in this article sounds familiar, the more useful first step is assessment of the condition itself. Our overview of how liposuction is assessed and planned explains what a surgical consultation involves once a diagnosis is clear.
Frequently asked questions
How do I know if it is lipedema or just fat?
The distinguishing features are symmetry, sparing of the hands and feet, pain or tenderness, easy bruising, a nodular tissue texture, and disproportionate resistance to weight loss. Ordinary fat is not painful and does not stop abruptly at the ankle. Only a clinician can make the diagnosis, since several conditions overlap.
Can lipedema legs be slimmed down?
Weight loss reduces the ordinary fat sitting on top of lipedema tissue, so some improvement is possible, but the affected tissue itself is comparatively resistant. Many people find their upper body responds while the legs change relatively little.
What is often mistaken for lipedema?
Obesity and lymphoedema are the two most common. Obesity is usually more proportionate and not painful. Lymphoedema more often involves the feet, is frequently one-sided, and is associated with a positive Stemmer sign. Lipedema and lymphoedema can also occur together.
Does lipedema always get worse?
Progression is variable. Some people remain stable for long periods, others progress. Conservative management is used partly to slow deterioration, and the consensus work on tumescent liposuction has been framed around preventing progression.
Is liposuction for lipedema the same as cosmetic liposuction?
No. The technique is adapted to preserve lymphatic structures, it is often staged across multiple procedures, and the goal is symptom relief and function alongside contour rather than aesthetics alone.
Will the fat come back after liposuction for lipedema?
Removed fat cells do not regenerate, but lipedema is a chronic condition and further accumulation over time is possible. Continued conservative management is generally advised rather than treating surgery as an endpoint.
Do men get lipedema?
It is far less common in men but has been described in the literature, including recent case series. It is more often associated with particular hormonal or hepatic conditions when it does occur.
Is lipedema the same as cellulite?
No. Cellulite is a surface dimpling caused by fibrous tethering bands and affects most adult women regardless of weight. Lipedema is a distinct disorder of fat tissue involving pain, symmetry, bruising and diet resistance.
The practical takeaway
If your legs or arms have enlarged symmetrically, feel tender or bruise easily, stop abruptly at the ankle or wrist, and have not responded to years of dieting, that pattern is worth having assessed rather than accepting as a personal failing.
Lipedema is a recognised condition with a recognised management pathway. Conservative measures come first and continue indefinitely. Lymph-sparing liposuction is the main surgical option, with reported long-term symptom benefit but an evidence base that is still developing. What matters most is getting the diagnosis right, because the answer to diet-resistant fat is different depending on what is actually causing it.