

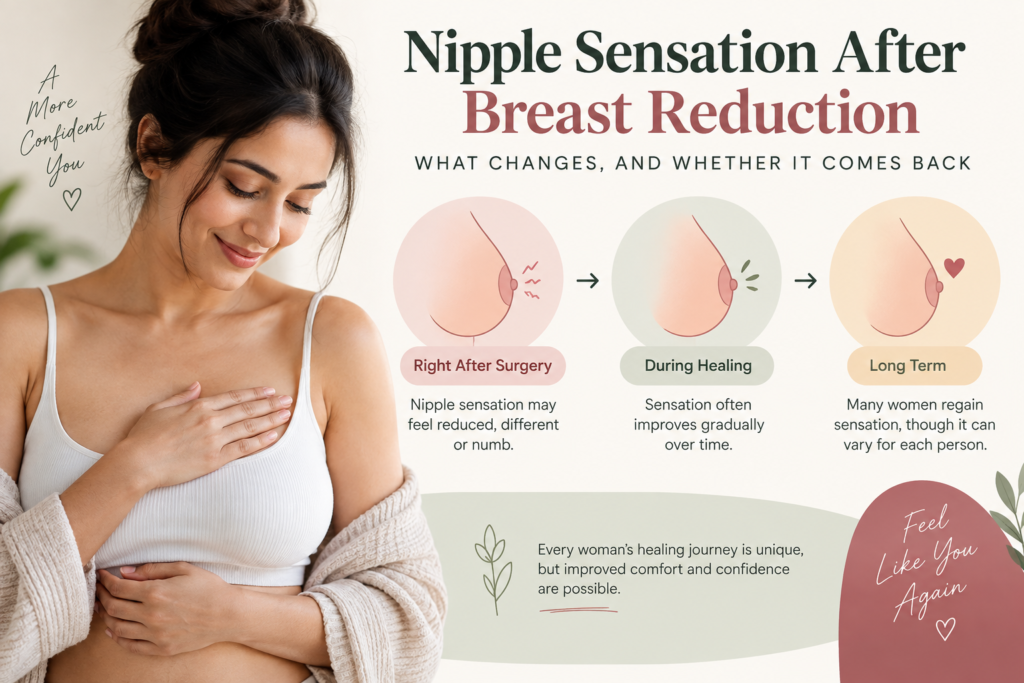
Reduced or altered nipple sensation after breast reduction is common in the early months and, for most people, improves substantially over the first year.
Sensation is rarely lost entirely, because the nipple remains attached to a pedicle of tissue that carries both its blood supply and its nerve supply. What is usually affected is the fine sensory nerve network within the tissue that was removed or repositioned.
Some degree of permanent change is possible, and this varies between individuals. It is a recognised outcome of the procedure rather than a complication, and it should be discussed before surgery rather than discovered afterwards.
Where nipple sensation comes from
Understanding the anatomy makes the rest of this predictable.
Sensation to the nipple-areola complex is supplied principally by branches of the intercostal nerves running between the ribs, with the lateral cutaneous branch of the fourth intercostal nerve commonly described as the dominant contributor. These nerves travel through breast tissue to reach the nipple.
That last point is the crux. The nerve supply does not arrive at the nipple through the skin surface; it travels through the tissue that breast reduction removes and rearranges. Any procedure that removes substantial breast volume therefore involves some disturbance to that pathway.
Surgeons address this by keeping the nipple attached to a pedicle: a column of tissue left deliberately intact to carry blood supply and nerves. Which pedicle is used is one of the main technical decisions in the operation, and it has consequences for sensation.
Why sensation changes immediately after surgery
Most people notice altered sensation as soon as the anaesthetic wears off. Several mechanisms contribute.
Stretch and handling. Nerves that remain anatomically intact can stop conducting normally after being stretched or manipulated. This temporary conduction block is described as neuropraxia and typically recovers.
Division of small branches. Fine sensory branches within removed tissue are unavoidably divided. Surrounding nerves often compensate over time.
Swelling. Oedema places pressure on nerves and distorts tissue, contributing to numbness that improves as swelling resolves.
Repositioning. Moving the nipple to a new position changes the geometry of the nerve pathway even when the nerves themselves are preserved.
These have different timelines, which is why sensation often changes in stages rather than returning all at once.
What the research shows about recovery
Sensation after reduction mammoplasty has been studied reasonably extensively, though with some important limitations.
Studies comparing pedicle techniques have found differences in sensory outcomes. Work comparing vertical pattern superomedial pedicle reductions with Wise pattern inferior pedicle reductions reported a higher rate of patients noticing decreased sensation in the superomedial group than the inferior pedicle group. Other studies examining medial versus inferior pedicle approaches have reported high rates of preserved total nipple-areola sensation in both, with the inferior pedicle performing somewhat better.
On timing, a controlled trial comparing pedicle techniques found that several measures of pain sensation and two-point discrimination were significantly reduced at three months but had normalised by six to twelve months. Crude touch sensation was reduced in the superomedial pedicle group at three and six months, with recovery by twelve months.
The broad pattern across this literature is that early reduction in sensation is common, and recovery over six to twelve months is usual.
Two caveats deserve stating. A scoping review has noted considerable heterogeneity in how nipple-areola sensation is assessed and reported across studies, which makes direct comparison between them difficult. And measured sensation and perceived sensation are not the same thing — someone can test normally and still feel different, or vice versa.
How technique affects sensation
This is worth understanding before your consultation, because it is a legitimate question to ask.
| Approach | Nipple remains attached? | General expectation for sensation |
|---|---|---|
| Inferior pedicle | Yes, on tissue below the nipple | Frequently reported as favourable for sensory preservation |
| Superomedial pedicle | Yes, on tissue above and medial | Some studies report higher rates of reported decrease early on |
| Medial pedicle | Yes, on tissue medial to the nipple | High rates of preserved sensation reported |
| Free nipple graft | No — nipple fully detached and grafted | Sensation is generally significantly and often permanently reduced |
The free nipple graft is the important exception. It is generally reserved for very large reductions or specific clinical circumstances where keeping the nipple on a pedicle would risk its blood supply. Anyone for whom this technique is proposed should have the sensory implications explained clearly, because they differ substantially from pedicle techniques.
Technique is not chosen on sensation alone. Breast size, degree of ptosis, tissue quality, how far the nipple needs to move and the surgeon’s experience all factor in. Our guide to the surgical techniques and incision patterns used in breast reduction explains how those decisions are made.
Other factors that influence outcome
- Resection weight. Larger reductions generally involve more tissue disturbance.
- How far the nipple is moved. Greater repositioning distance means more change to the nerve pathway.
- Starting breast size and ptosis. Very large or significantly ptotic breasts may already have altered baseline sensation from tissue stretch.
- Individual anatomy. Nerve distribution varies between people.
- Healing factors. Smoking, diabetes, and complications affecting the nipple can all influence sensory recovery.
- Age. Nerve regeneration tends to be slower with increasing age, as with healing generally.
Two different kinds of sensation
A distinction that gets lost in most discussions and matters to different people for different reasons.
Protective sensation is the ability to feel touch, pressure, temperature, and pain. It has a safety function: knowing when something is hot, sharp, or pressing too hard. Loss of protective sensation means taking more care around heat sources and checking skin visually.
Erogenous sensation relates to sexual response and is not the same neurological pathway experience as protective touch. Studies have examined sensitivity of the nipple-areola complex alongside sexual function after reduction, reflecting that this is a genuine consideration for patients rather than a peripheral one.
It is entirely possible to recover protective sensation while erogenous sensation remains altered, or the reverse. If this matters to you — and for many people it does — it is a reasonable and appropriate thing to raise before surgery. Surgeons discuss it routinely.
Increased sensitivity, not just numbness
Numbness gets the attention, but the opposite also occurs and surprises people who were only warned about one direction.
Hypersensitivity, tingling, shooting or burning sensations, and general oversensitivity to touch or clothing are all reported during recovery. These typically reflect nerves regenerating rather than nerves failing, and they usually settle as recovery progresses.
Sensations described as electric, zapping, or prickling are commonly reported as sensation returns and are generally a sign of activity rather than damage. Persistent or worsening pain is a different matter and should be assessed.
When to raise it with your surgeon
Altered sensation in the months after surgery is expected. Some situations warrant earlier contact.
- Sensation that was improving and then deteriorates
- Numbness accompanied by colour change in the nipple or areola, particularly in the early post-operative period
- Severe or worsening pain rather than the settling discomfort of recovery
- Any wound problem affecting the nipple or areola
- Marked asymmetry between the two sides that is not improving
- Sensation that has not changed at all by around a year, if it matters to you and you want it assessed
Our overview of what breast reduction involves from procedure through recovery covers the wider picture, and key facts worth knowing before the procedure is useful pre-consultation reading. To discuss your own case, our page on breast reduction assessment and consultation explains what an appointment involves.
Frequently asked questions
Is nipple numbness normal after breast reduction?
Yes. Reduced or altered sensation in the early weeks and months is common and expected, reflecting nerve stretch, swelling and division of small sensory branches during surgery.
Does nipple sensation come back after breast reduction?
For most people, it improves substantially. Studies measuring sensory recovery have found several measures significantly reduced at three months but normalised by six to twelve months. Some degree of permanent alteration is possible and varies individually.
How long does numbness last?
Improvement typically occurs over months rather than weeks, with the six-to-twelve-month window being where most measured recovery is reported. Sensation can continue changing gradually beyond a year.
Can breast reduction cause permanent loss of nipple sensation?
Permanent alteration is possible and is a recognised outcome that should be discussed during consent. It is considerably more likely where a free nipple graft technique is used, since the nipple is fully detached in that approach.
Does the surgical technique affect sensation?
Yes. Studies comparing pedicle techniques have reported differences, with inferior and medial pedicle approaches generally associated with favourable sensory preservation. Technique is chosen on multiple clinical grounds, not sensation alone.
Why does my nipple feel hypersensitive rather than numb?
Hypersensitivity, tingling and shooting sensations commonly accompany nerve recovery and usually settle. This is a different experience from numbness but reflects the same underlying process.
Will sensation change affect breastfeeding?
Sensory nerves and the structures involved in lactation are related but distinct considerations, and both can be affected by breast surgery. If future breastfeeding matters to you, raise it specifically before surgery, as it may influence technique selection.
Is there anything I can do to improve sensory recovery?
There is no established intervention that reliably accelerates sensory nerve recovery. General factors that support healing not smoking, good nutrition, well-controlled medical conditions, and following aftercare instructions are a sensible approach.
The practical takeaway
Altered nipple sensation after breast reduction is common, usually temporary, and largely explained by anatomy: the nerves reach the nipple through the tissue the surgery removes and rearranges.
Most measured sensory change recovers within six to twelve months, and technique influences the likelihood of change. Some permanent alteration is possible, which is why it belongs in the pre-surgery conversation rather than being discovered afterwards.
If sensation matters to you for safety, for intimacy, or simply because it is part of how your body feels, say so before surgery. It is a normal thing to ask about, and it can genuinely inform the surgical plan.